What Is the Urine Anion Gap?
The urinary anion gap is a basic way to estimate how the kidneys are processing acid-related substances in the urine. It uses urinary electrolytes—mainly sodium, potassium, and chloride—to help infer whether the kidneys are excreting enough acid through ammonium excretion. In clinical practice, it is less about spotting a single number and more about understanding acid-base status and kidney function in context.
Think of it as a lab marker that gives insight about renal acid handling and urine chemistry. When the body develops an acid-base disorder, the kidneys normally respond by increasing kidney acid excretion. The urine anion gap helps gauge whether that response is happening properly.
Although the name includes “anion gap,” this is not the same as the serum anion gap used on an electrolyte panel. The urine version is calculated from urine measurements and is mainly used in the evaluation of metabolic acidosis, especially normal anion gap metabolic acidosis.
What Is the Urine Anion Gap Used For?
The main use of the urine anion gap is to help determine whether the kidneys are appropriately increasing ammonium excretion during metabolic acidosis. This is useful when clinicians need to tell apart a gastrointestinal cause of bicarbonate loss, such as diarrhea, and a renal cause, such as renal tubular acidosis.
Simply put, the test helps answer a practical question: is the problem coming from the gut or the kidneys? This is what makes it helpful in the differential diagnosis of normal anion gap metabolic acidosis. If the kidneys are functioning normally, they should enhance acid removal by making and excreting ammonium, which often makes the urine anion gap more negative.
It is also clinically useful in suspected renal tubular acidosis, including distal renal tubular acidosis and proximal renal tubular acidosis. In these settings, the urine anion gap can support the diagnosis by suggesting impaired renal acidification. It is therefore part of a broader metabolic evaluation and not a standalone verdict.
Because the result reflects kidney function and urinary acidification, it is most helpful when a clinician is trying to interpret systemic acidosis with a normal serum anion gap. It is of limited value in mixed disorders or when the urine chemistry does not reflect the underlying physiology well.
How the Urine Anion Gap Is Calculated
The standard calculation uses urine sodium and urine potassium subtracting urine chloride:
Urine anion gap = urine sodium + urine potassium - urine chloride
This is an anion calculation calculated from measured laboratory values. The result is used as an indirect estimate of unmeasured urinary ions, especially ammonium. A commonly used anion gap calculator may assist with the arithmetic, but the interpretation still depends on the clinical picture and the type of acid-base disorder being evaluated.
When the urine chloride is relatively high compared with urine sodium and urine potassium, the urine anion gap tends to be negative. That often suggests higher ammonium excretion. When chloride is low relative to the other urinary electrolytes, the urine anion gap tends to be positive, which may suggest impaired renal acid excretion.
Even though the formula is easy to apply, the meaning is not purely mathematical. The result is a proxy for renal response during an electrolyte imbalance, and its usefulness depends on the quality of the urine sample, timing of collection, and the patient’s overall metabolic state.
Reading Raised, Negative, and Neutral Values
Assessment of the urine anion gap usually opens with the sign of the number:
- Positive urine anion gap: commonly points to lower ammonium excretion and reduced renal acidification. Reduced urine anion gap: often suggests enhanced ammonium excretion and normal renal response. Near-zero or near-zero values: may be indeterminate or unclear and need clinical context.
A positive urine anion gap is frequently seen with a renal cause of acidosis, especially renal tubular acidosis. In this context, the kidneys are not removing enough acid, so ammonium does not rise as expected. That makes the urine anion gap a practical clue, not a final diagnosis.
A reduced urine anion gap usually suggests appropriate ammonium production. That can happen when acidosis is driven by outside the kidney bicarbonate loss, such as diarrhea. In these cases, the kidneys are adapting by boosting ammonium excretion, which shifts the urine chemistry in the negative direction.
The role of unmeasured positive ions and unmeasured negative ions matters here. The urine anion gap is only an indirect estimate. If unusual substances are present in the urine, the number may not reflect ammonium accurately. The same applies if the urine sample is watered down or otherwise altered by treatment or physiology.
Because ammonium is not directly measured in many routine settings, the urine anion gap acts as a practical surrogate. That makes it useful, but also inexact. Interpretation should always be tied to the patient’s acid-base status, kidney function, and the broader diagnostic workup.
Urine Anion Gap vs Serum Anion Gap
The serum anion gap and the urine anion gap address out different questions. The serum version helps distinguish high anion gap metabolic acidosis versus normal anion gap metabolic acidosis. The urine version helps determine whether the kidneys are adequately responding to the acid load.
In a high anion gap metabolic acidosis, hidden acids are accumulating in the blood. This is typically evaluated with serum chemistry and a larger metabolic workup. In contrast, a normal anion gap metabolic acidosis often reflects bicarbonate loss or defective renal acidification, which is where the urine anion gap becomes especially useful.
So, the serum anion gap helps pinpoint the category of systemic acid-base problem, while the urine anion gap helps trace the source of the issue. One is more about the blood; the other is more about kidney response and urine chemistry. Used together, they improve clinical interpretation and sharpen the differential diagnosis.
Both tests are part of broader acid-base disorders assessment. A clinician may use the serum anion gap first, then use the urine anion gap when the pattern suggests a kidney versus gastrointestinal source of acidosis.
Common Clinical Scenarios
Many everyday clinical scenarios make the urine anion gap useful. The most frequent is diarrhea, which can cause bicarbonate loss and lead to normal anion gap metabolic acidosis. In this situation, the kidneys should compensate by increasing ammonium excretion, often producing a negative urine anion gap.
A further classic scenario is renal tubular acidosis. In distal RTA, the distal nephron cannot acidify urine properly, so acid excretion is impaired. This often leads to a positive urine anion gap because ammonium excretion is not appropriately increased. The test can support the diagnosis when paired with other findings.
Proximal RTA is different. Here, bicarbonate reabsorption is impaired in the proximal tubule, leading to bicarbonate wasting. The urine anion gap may be less straightforward to interpret because the kidney’s ammonium response can vary depending on the phase of the disorder and the patient’s overall acid-base state.
In all of these examples, the urine anion gap is not used alone. It is one part of a diagnostic test sequence that includes serum electrolytes, urine studies, and the clinical history. Its value lies in helping separate renal from nonrenal causes of metabolic acidosis.
A practical way to view about it: if acidosis is present and the kidneys are responding normally, the urine anion gap often becomes negative. If the kidneys are failing to acidify the urine, it is more likely to be positive.
Limitations and Challenges
The urine anion gap has important drawbacks. One major issue is volume depletion, which can alter urine sodium and urine chloride values enough to affect interpretation. If the urine is highly concentrated or the patient is dehydrated, the numbers may not reflect usual kidney handling of acid.
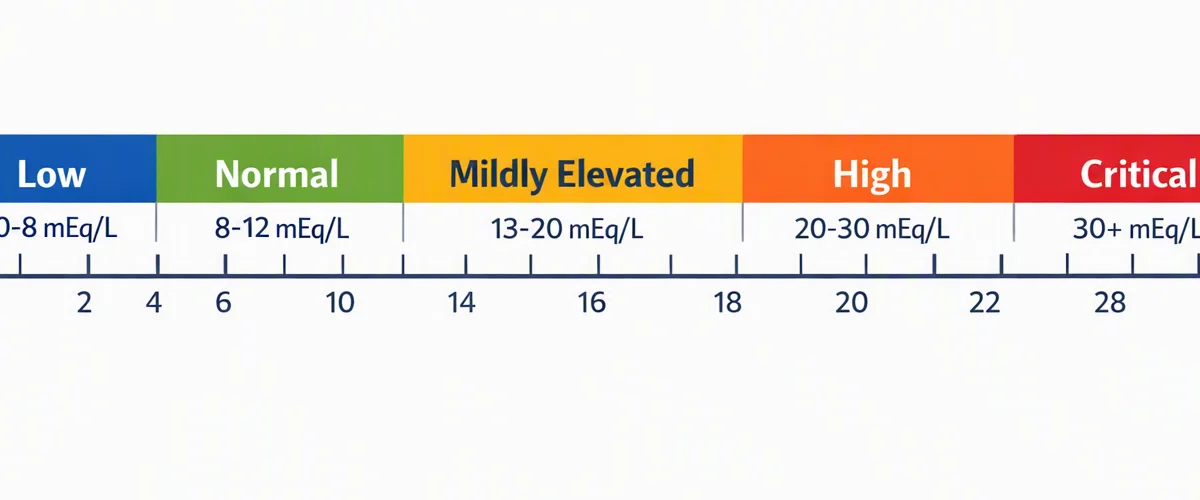
Another problem is reliance on urine chloride alone without considering the full context. Since the formula depends on chloride relative to sodium and potassium, any condition that alters urine chloride can shift the result. This is why interpretation must account for the patient’s diet, fluids, and current treatment.
Kidney disease can also cloud the picture. When renal function is reduced, urine chemistry may not behave predictably, and ammonium excretion may be affected for reasons beyond classic renal tubular disorders. That makes the urine anion gap less reliable in advanced disease or complex renal syndromes.
Measurement error is another concern. Because the calculation depends on routine laboratory values, small inaccuracies can influence the final number. Specimen handling, timing, and assay differences can all affect the result. For that reason, the urine anion gap should be viewed as a adjunctive clue rather than a definitive diagnostic test.
There are also cases where the result can be misleading because of unusual unmeasured cations or unmeasured anions in the urine. When that happens, the link between the calculated value and true ammonium excretion becomes NAGMA causes weaker. This is why a full acid-base evaluation matters more than a single number.
When to Use an Anion Gap Calculator
An anion gap calculator is valuable when you want a fast, structured way to carry out the arithmetic and prevent simple errors. It can be useful during clinical decision-making, especially when checking an electrolyte panel or sorting through acid-base data as part of an acid-base evaluation.
For the urine anion gap specifically, a calculator can speed up the anion calculation using urine sodium, urine potassium, and urine chloride. That saves time in the middle of a diagnostic workup, but it does not replace judgment. The numbers still need careful review in light of symptoms, serum studies, and the broader pattern of electrolytes.
Using a calculator is most useful when the clinician suspects normal anion gap metabolic acidosis and wants to distinguish renal from gastrointestinal causes. HAGMA differential It is also useful when evaluating possible renal tubular acidosis or when the next step in the workup depends on whether ammonium excretion is likely preserved.
In short, the calculator supports the process; it does not make the diagnosis. The best use of the tool is as a rapid check during a careful metabolic evaluation.
FAQs About the Urine Anion Gap
What does a positive urine anion gap mean?
A positive urine anion gap usually suggests that the kidneys are not excreting enough ammonium. In the setting of metabolic acidosis, that raises concern for impaired renal acidification, such as renal tubular acidosis. It is a clue, not a complete diagnosis, and it should be interpreted alongside kidney function and the rest of the laboratory values.
When is the urine anion gap helpful in metabolic acidosis?
It is most helpful in metabolic acidosis with a normal serum anion gap, especially when clinicians need to separate renal causes from extrarenal bicarbonate loss. It can be particularly useful in suspected normal anion gap metabolic acidosis, diarrhea, and renal tubular acidosis. In these cases, it adds value to the diagnostic test strategy.
How is the urine anion gap different from the serum anion gap?
The serum anion gap is relied on to categorize blood acid-base abnormalities, including high anion gap metabolic acidosis. The urine anion gap is used to determine whether the kidneys are reacting properly by boosting ammonium excretion. One indicates blood chemistry; the other indicates urinary acid handling and kidney compensation.
Can diarrhea cause a negative urine anion gap?
Yes. Diarrhea can lead to bicarbonate loss and cause metabolic acidosis with intact renal response. In that setting, the kidneys usually enhance ammonium excretion, which often results in a negative urine anion gap. This pattern indicates an extrarenal cause rather than a primary kidney problem.
What are the limitations of using a urine anion gap?
The main limitations include volume depletion, abnormal urine chloride, kidney disease, and measurement error. The test also cannot directly determine ammonium in many routine settings, so it depends on indirect inference. Because of that, the urine anion gap should be interpreted as part of a broader clinical interpretation and not as a standalone answer to all diagnostic questions.