What Is the Anion Gap and How Is It Determined?
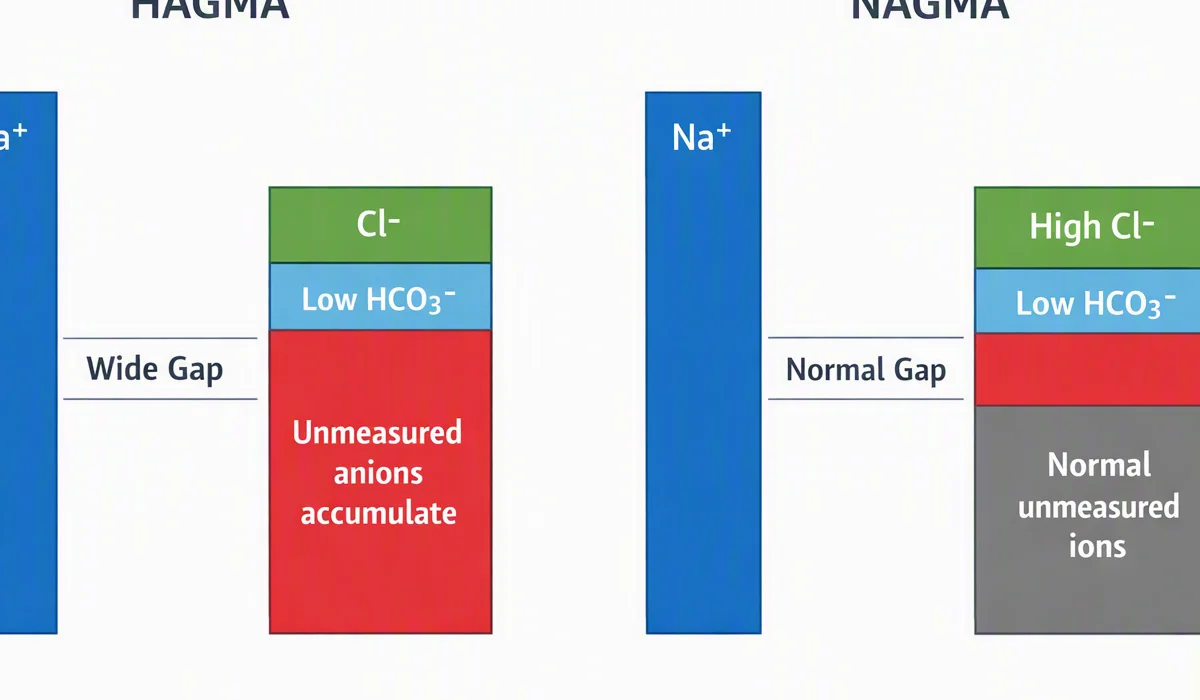
The anion gap is a calculated value that helps doctors evaluate acid-base balance and recognize an underlying metabolic acidosis. It represents the difference between the major measured cations and anions in the blood. In practical terms, it is obtained from the routine electrolyte panel using sodium, chloride, and bicarbonate.
The classic anion gap formula is:
anion gap = sodium - (chloride + bicarbonate)
Because this is a calculated value, it is affected by the accuracy of the underlying lab numbers. A unexpectedly high result suggests that unmeasured anions are present in the bloodstream. These may include organic acids, toxic metabolites, or other compounds that create an electrolyte disturbance and shift the body into an acidotic state.
Most clinicians also consider the role of albumin, the main unmeasured anion in blood. Low albumin can lower the apparent anion gap, so the raw number may underestimate the severity of an anion gap elevation. That is why interpretation always depends on the clinical setting, not the number alone.
The key idea is simple: the anion gap is not a diagnosis. It is a diagnostic clue that can point toward a process such as lactic acidosis, ketoacidosis, renal dysfunction, or toxin-related acidosis.
How an Anion Gap Calculator Helps Interpret Results
An Anion Gap Calculator makes it easier to apply the formula accurately and quickly. Rather than estimating the calculation by hand, a clinician or patient can enter the relevant laboratory values and get an prompt result. This can be useful when trying to decide whether a reported lab pattern fits a normal reference interval or suggests an abnormal acid-base process.
Beyond simple calculation, the best use of an Anion Gap Calculator is clinical interpretation. A number by itself rarely answers the full clinical question. The result should be viewed within the broader picture with symptoms, vital signs, medications, exposure history, and the rest of the chemistry panel.
Many calculators also include albumin correction. This matters because a low albumin level can mask a true gap. Correcting for albumin improves laboratory interpretation and helps avoid missing an important metabolic derangement. If albumin is low, a patient may have significant high anion gap metabolic acidosis even when the uncorrected value appears only somewhat elevated.
Using a calculator can also help separate a true metabolic problem from a reporting issue. For example, an electrolyte panel may show a borderline gap, but the presence of low bicarbonate, elevated lactate, or an abnormal blood gas may reveal a more serious process. The calculator therefore supports a broader pattern-recognition approach in place of replacing clinical judgment.
In toxin evaluation, the calculator can serve as an early screen. If the gap is elevated, clinicians may think about exposures that generate unmeasured anions. If the gap is normal but suspicion remains high, further testing may still be needed.
Can Toxins Increase the Anion Gap?
Absolutely. Certain poisons can raise the anion gap by generating acids, impairing metabolism, or triggering accumulation of toxic metabolites. This is a classic cause of high anion gap metabolic acidosis. In these cases, the body retains acidic compounds that are not directly measured on a standard panel, so the gap widens as bicarbonate drops.
A poison ingestion often causes more than one abnormality at the same time. The patient may have stomach upset, vomiting, dizziness, mental clouding, tachypnea, or increasing exhaustion. Lab results may show low bicarbonate, rising chloride changes, and an increased anion gap. The exact pattern depends on the agent involved and how long ago the exposure occurred.
The mechanism is often a form of metabolic acidosis caused by too much acid production or reduced acid removal. Some exposures directly produce acids, while others interfere with cellular respiration, creating lactic acidosis or other downstream effects. In all cases, the gap is an indicator of build-up of unmeasured acidic substances.
Notably, toxin-related acidosis is not limited to one poison. Several agents can lead to a comparable chemistry pattern, which is why exposure history and targeted testing are important. The anion gap provides an early clue, but not the full diagnosis.
Typical Toxic Origins of a High Anion Gap
Several toxins are traditionally linked to a high gap. The most important include methanol, ethylene glycol, and salicylates, along with conditions that produce lactic acidosis. These problems can be life-threatening and may present with nonspecific poisoning symptoms.
Methanol is particularly dangerous because it is metabolized into acidic compounds, including formic acid. This leads to acidosis and may also affect vision and the central nervous system. An elevated gap in the setting of exposure history should raise immediate concern.
Ethylene glycol, found in some antifreeze products, is metabolized into glycolic acid and other acids. These toxic metabolites can drive a sharp rise in the anion gap and create kidney injury, neurologic changes, and worsening acidosis.
Salicylates can produce a mixed and evolving picture. Early on, respiratory alkalosis may dominate, but as toxicity progresses, a high gap metabolic acidosis may emerge. Because of this, the lab pattern can change over time and may not be obvious on a single sample.
Lactic acidosis is another major contributor to a high gap. Although not always caused by an external toxin, it can result from impaired tissue oxygen use, shock states, seizures, or severe poison exposure. In toxin evaluation, rising lactate is a major clue that cells are struggling to generate energy normally.
Further poisonings can also contribute, but these are among the most clinically important because they are common, dangerous, and treatable when recognized early. A high gap should prompt consideration of the exposure timeline, associated symptoms, and confirmatory testing.
How Poisonous Alcohols Impact pH equilibrium
Harmful alcohols remain among the most important triggers of marked anion gap rise. This category includes methanol and ethylene glycol, each of which can first look misleadingly mild before major metabolic injury develops. Their danger comes from metabolism into very acidic compounds.
These substances also often produce an elevated osmolar gap early in the course. The osmolar gap indicates extra osmoles in the blood and can be valuable when a toxic ingestion is suspected. With time, as the parent alcohol is metabolized, the osmolar gap may decrease while the anion gap rises. This pattern is a major diagnostic clue.
With methanol, the critical toxic metabolite is formic acid. Formic acid contributes to metabolic acidosis and can injure the optic nerve, which is why visual symptoms may be important. With ethylene glycol, glycolic acid and related metabolites drive acidosis and renal injury.
The acid-base effect is more than a lab curiosity. It reflects a genuine physiologic emergency in which toxic metabolites accumulate, buffering systems are overwhelmed, and the patient enters a progressively worse acidotic state. That is why treatment decisions often are based on the combination of symptoms, exposure history, blood gas results, and the gap pattern.
In some cases, a patient may have both an elevated osmolar gap and a high anion gap metabolic acidosis. That combination powerfully indicates toxic alcohol exposure and demands immediate action. However, neither number alone is sufficient to rule in or exclude the diagnosis.
Additional Poisoning Events and Disorders That Raise the Anion Gap
Not every increased gap is caused by toxic alcohols. Many other processes can produce the same picture, including ketoacidosis, renal failure, uremia, and cyanide exposure. These conditions all create accumulation of acids or limit the body’s ability to clear them.
Ketoacidosis occurs when ketone production rises faster than the body can use them. This can happen in diabetes, prolonged fasting, or heavy alcohol use. Ketones are organic acids, so they raise the gap and decrease bicarbonate.
Renal failure can also elevate the gap because damaged kidneys cannot remove acids effectively. When waste products build up, uremia develops, and the patient can progress into metabolic acidosis. This is one reason kidney function is a component of the standard evaluation for unexplained acidosis.
Cyanide is particularly dangerous because it prevents cellular oxygen utilization. Even if oxygen is present in the blood, cells cannot use it properly, which can rapidly cause severe lactic acidosis. In this setting, the anion gap may climb as lactate accumulates.
This range of causes matter because a high gap is not exclusive to ingestion. It can also indicate internal illness, tissue hypoperfusion, or organ failure. The challenge is determining whether the pattern reflects a toxin-related emergency or another severe cause of acid-base disruption.
When a Normal Anion Gap Does Not Rule Out Poisoning
A normal anion gap does not dismiss poisoning. This is especially true in early poisoning, when the toxic substance has not yet been fully metabolized into acidic byproducts. In that window, the gap may still look normal even while the patient is worsening clinically.
Another reason for a misleading result is a mixed acid-base disorder. For example, a patient may have one process increasing the gap and another process lowering it, producing a net value that appears deceptively normal. Nausea and vomiting, hyperventilation, renal disease, or treatment given before labs are drawn can all affect the final number.
That is why clinical suspicion remains essential. Symptoms, timing, access to toxic substances, mental status, and lab trends matter more than a single snapshot. If the history suggests ingestion, clinicians should not dismiss the possibility simply because the anion gap is not elevated yet.
This point is especially important with toxic alcohols and salicylates, where the laboratory picture can evolve over time. Repeating labs may reveal a developing anion gap elevation even if the first sample is unrevealing.
In short, the gap is a helpful clue, but a normal result is not a guarantee of safety.
Which Tests Are Used Alongside the Anion Gap?
When toxin-related acidotic imbalance is thought to be present, the anion gap is merely one part of the workup. A blood gas analysis helps assess pH, bicarbonate status, and whether the body is in an acid-buildup state. It additionally helps determine whether a respiratory component is present.
Serum lactate is often checked because high lactate can help explain a high gap and point toward tissue reduced blood flow, convulsions, or toxin exposure. Increasing lactate may also signal marked cellular stress and progressive metabolic derangement.
Ketones matter if ketoacidosis is possible. Checking ketones can help separate diabetic ketoacidosis, starvation ketosis, or alcohol-related ketosis from other causes of metabolic acidosis.
A tox screen may also be useful, although common screens do not detect every toxin. Additional testing for methanol, ethylene glycol, salicylates, or other substances may be needed based on the patient history and first lab results. For this reason targeted testing and indirect clues often work together.
Extra evaluations may include kidney function studies, osmolality checks, and repeated electrolyte measurements. The overall goal is to combine the anion gap with the rest of the results so the likely source can be identified quickly and care can begin.
When You Should Seek Urgent Medical Evaluation
Immediate evaluation is important when toxin ingestion is suspected and symptoms indicate critical illness. Warning signs include altered mental status, worsening breathing, intense vomiting, fainting, seizures, visual changes, or sudden confusion. These may suggest a life-threatening acid-base disorder or ongoing poisoning.
If you are worried for ingestion, contact poison information without delay and obtain emergency treatment if symptoms are worsening. Immediate care can have a major impact in outcomes for toxic alcohols, salicylates, cyanide, and anion gap or osmolar gap differences other poisons.
People should not hold off for symptoms to become severe if the exposure is known or seriously suspected. Even before a definitive diagnosis is confirmed, the combination of clinical history, a high anion gap, and supportive lab findings can justify immediate action.
A useful approach is to treat the anion gap as one piece of a larger picture. If the number is elevated, the patient may need more testing and urgent management. If the number is within range but suspicion remains high, re-evaluation is still necessary because poisoning can change fast.
FAQ
What toxins most commonly increase the anion gap?
The most common toxin-related causes include methanol, ethylene glycol, and salicylates. These can produce high anion gap metabolic acidosis through toxic metabolites, acid accumulation, or both. Severe lactic acidosis from poisoning or tissue injury can also raise the gap.
Can a normal anion gap still happen with poisoning?
Absolutely. A normal anion gap can occur in early poisoning or in a mixed acid-base disorder that masks the abnormality. If clinical suspicion is high, the patient may still need follow-up labs and focused toxicology testing.
How does an Anion Gap Calculator help with toxin evaluation?
An Anion Gap Calculator efficiently calculates the anion gap formula to the patient’s laboratory values. It helps recognize whether the result is outside the expected reference interval, helps detect anion gap elevation, and can be paired with albumin correction for better laboratory interpretation.
What is the difference between anion gap and osmolar gap?
The anion gap calculates unmeasured anions and is useful for detecting metabolic acidosis. The osmolar gap calculates unmeasured osmoles and is especially helpful in suspected toxic alcohols. In some NAGMA causes poisonings, the osmolar gap is high early, while the anion gap rises later as toxic metabolites such as formic acid and glycolic acid build up.
When should someone get immediate medical attention for suspected toxin exposure?
Obtain immediate medical attention at once for potential toxin poisoning with confusion, trouble breathing, convulsions, severe vomiting, vision changes, or passing out. Contact poison control right away as well. These symptoms may signal a critical acid-base disorder that needs urgent assessment and treatment.